
Surgical care
Metabolic and Bariatric Surgery
Metabolic surgery treats physiology. Your body defends a set point through hormones, hunger signals, and how it stores fuel. Surgery changes those signals. It is not a willpower intervention and it is not a shortcut. The number on a scale is not the goal. Health is.
Surgery is performed at The Center for Bariatric Surgery at AdventHealth Parker. An accredited center of excellence through the Metabolic and Bariatric Surgery Accreditation and Quality Improvement Program of the American Society for Metabolic and Bariatric Surgery and the American College of Surgeons.

Robotic Sleeve Gastrectomy
Robotic means the operation is done through several small openings in the abdomen instead of one long one. A camera goes through one of them. Long thin instruments go through the others. I work from a magnified view of the field.
During the operation I remove the outer curve of the stomach and shape what remains into a narrow tube. The staple line closes it. The stomach holds less, and that is the part people already know about.
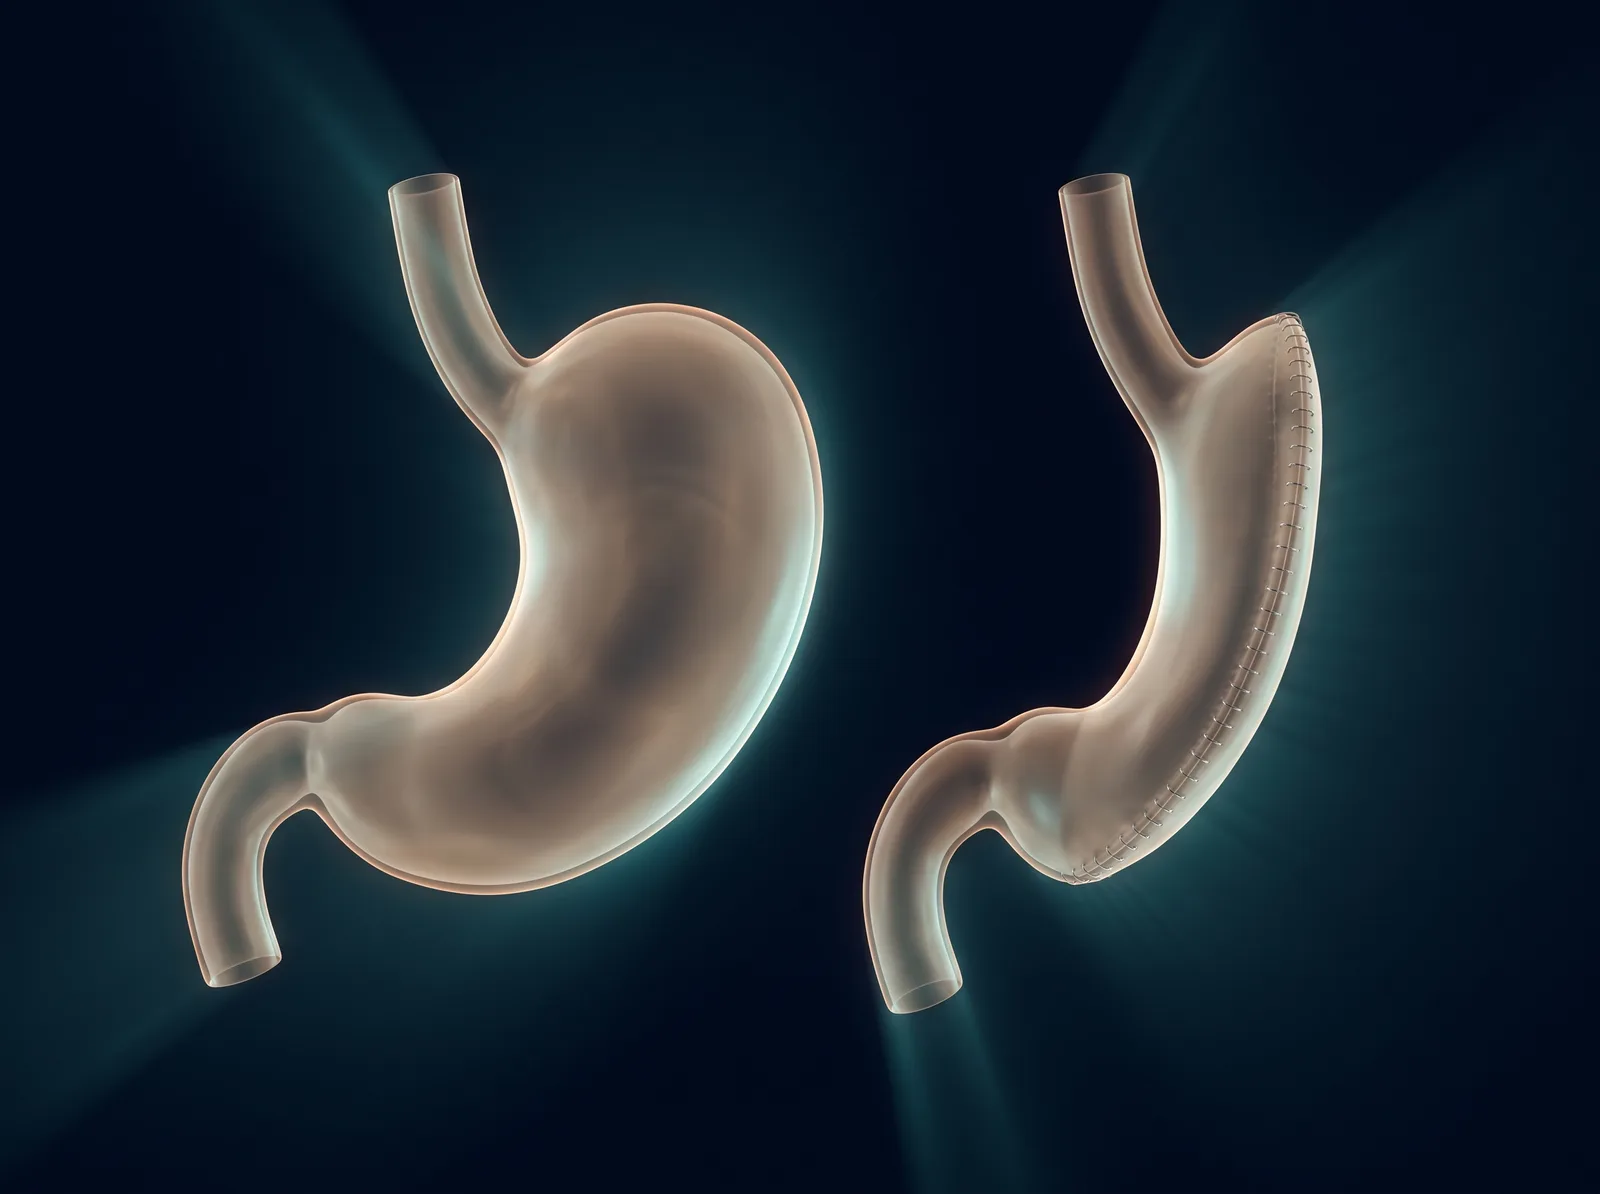
The part that matters more is hormonal. The section of stomach that comes out is a busy signaling organ. It produces hormones that drive hunger and influence how your body handles blood sugar and stores fuel. Remove it and those signals change. Hunger usually quiets. Blood sugar control often improves early, before much has changed on a scale.
That is the reason this is called metabolic surgery.
Reflux is one of several factors weighed during the pre-operative evaluation. The older idea that a sleeve automatically produces significant reflux, and that reflux risk by itself means you should have a bypass, is not supported by current practice. The evaluation is what determines which procedure fits you.
The change is permanent. That part of the stomach does not grow back, and this is not a device that can be removed or reversed later. It is a real decision, and you should make it with full information and without pressure.
Robotic Roux-en-Y Gastric Bypass
The gastric bypass creates a small stomach pouch at the top of the stomach and connects it directly to a segment of small intestine. Food then bypasses the rest of the stomach and the first part of the small intestine. The bypassed stomach stays in place and keeps making digestive juices, which join the food further down.
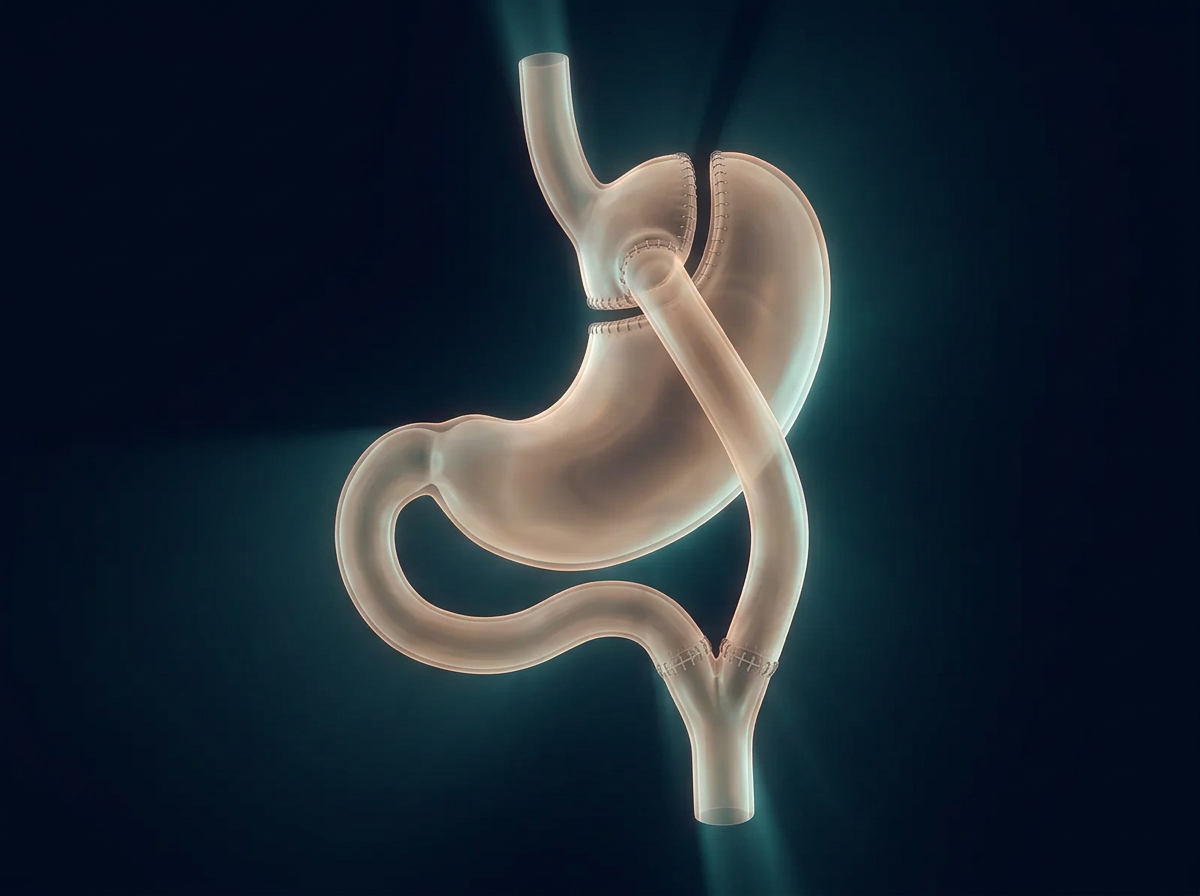
As with the sleeve, the part that matters most is hormonal. Changing the route food travels changes the signals from the gut that govern hunger, fullness, and how your body handles blood sugar. Blood sugar control often improves early, before much has changed on a scale.
Reflux is weighed in the evaluation. Because the bypass routes acid and bile away from the esophagus, it is one of the options discussed when reflux is a significant part of the picture.
It asks more of you afterward, in supplementation and in monitoring. Vitamins and minerals are taken for life, labs are checked on a schedule, and some medications, such as anti-inflammatory pain relievers, are avoided. Whether it is the better fit is decided by your evaluation, not by reputation.
Over time the outlet between the pouch and the intestine can stretch. For some patients, that can be addressed endoscopically with transoral outlet reduction (TORe).
Revisional Bariatric Surgery
Some patients come in after an earlier operation that is no longer serving them. The first step is finding out why, with imaging, endoscopy, and a review of what was done before.
Revision is a second operation on anatomy that has already been changed. It is planned carefully and it is not offered reflexively.
For some patients with a prior gastric bypass, an endoscopic option called transoral outlet reduction (TORe) may be considered.
Gastric Lap-Band
The practice is happy to evaluate any patient who has a gastric band or is considering one. Evaluation comes first.
If you have a gastric band and it is causing trouble, bring any records you have. We start by finding out what the gastric band is doing before deciding what comes next.
Is Surgery Right For You
Candidacy is a medical decision, and it is made after an evaluation, not from a form or a single measurement.
The evaluation looks at your metabolic health and what is driving it, the conditions you are being treated for, your medications, what you have already tried and what happened, your reflux and swallowing history, prior abdominal operations, and how safely you would come through anesthesia.
It is also a conversation about what you want. Surgery asks something of you afterward. If you are being pushed toward it by someone else, that is worth saying out loud in my office.
Sometimes the answer is that an operation is not the right treatment right now, or at all. That is not a rejection and it is not the end of your care. You will leave with a plan either way.
Who it is for
People whose metabolic health is not responding to medication and structured change, and whose evaluation points to surgery as the treatment that fits.
People with conditions driven by metabolic disease, where treating the underlying physiology changes the whole picture rather than one measurement.
People who want a partner for the long run. Surgery is one step in ongoing care, not the end of it.
What to expect
Before. A full evaluation comes first, including testing where it is needed.
The day of. The operation is done through small incisions in the abdomen. The procedure is performed under anesthesia. The anesthesia team will discuss expected comfort, awareness, recovery, and risks with you.
After. You move through a staged diet and return for scheduled follow-up. We track how you feel, how you are eating, and how your metabolic health is responding. That care continues.
Common questions
Ready to talk it through?
Request a consultation and we will respond within one to two business days.
Request for Information